CJC-1295 / Ipamorelin
CJC-1295 / Ipamorelin is a blend of two peptides that signal the body to release its own growth hormone. Neither is FDA-approved, and no trial has tested the blend itself. CJC-1295 copies the brain’s release signal for growth hormone. Ipamorelin copies ghrelin, a hunger hormone that also triggers growth-hormone release.
What it’s studied for
- Higher growth hormoneStudied in humans
In healthy adults, a long-acting form of CJC-1295 raised growth hormone 2 to 10 times. That form is not the one in the blend. source
- Two signals togetherStudied in humans
In a small human study, the two signal types together released more growth hormone than either would alone. source
- Clean releaseStudied in animals or lab
In lab and animal work, ipamorelin released growth hormone without raising the stress hormone cortisol. source
2 more uses studied
- Better sleepReported by users
Usually the first change users describe, within 1 to 2 weeks.
- Faster recoveryReported by users
Users describe less soreness and quicker recovery after 2 to 4 weeks.
 New here? Three things worth knowing first
What’s a peptidepeptideA short chain of amino acids. Proteins are long chains; peptides are short ones, usually under 50 amino acids.? A short chain of amino acids, the building blocks of protein. Many act like messengers in the body.
Why the vial has to be mixed. It ships as a dry powder. You add bacteriostatic waterbacteriostatic waterSterile water with a little benzyl alcohol that stops bacteria growing, so a mixed vial lasts days or weeks. Often called BAC water., and the amount you add decides how many unitsunitsMarks on an insulin syringe. On a U-100 syringe, 100 units = 1 mL. How many units equal a dose depends on how much water was added. on the syringe equal one dose. The calculator does that math.
SubcutaneoussubcutaneousUnder the skin, into the fat layer. The usual route for peptide injections. Often shortened to sub-Q. injection, Once daily, every day. Subcutaneous means into the fat layer just under the skin. It uses a small insulin syringe. Any word with a dotted underline on this page opens a short definition.
Dosage guidelines
Once a day, on an empty stomach, often before bed. Doses run 200 to 600 mcg of the blend, in 12 to 16 week cycles with 4 weeks off.
The doses below come from published reference protocols and, where they exist, the human trials. Tap a row to load it into the calculator.
Figures reviewed against their sources in October 2026. Where a trial or approved label sets a schedule, it is shown first; where a label sets one fixed dose, the FAQ below says so.
Standard protocol. 200 to 600 mcg of the blend once a day, fasted. Cycles run 12 to 16 weeks, then 4 weeks off. Each dose is half of each peptide.
General optimization and fat loss · 200–600 mcg of blend (100–300 mcg of each peptide), once daily, every day · 12–16 weeks
| Step | Dose per injection | Draw to | |
|---|---|---|---|
| 1 | 200 mcg (0.2 mg) between 5-unit marks | 4 units | |
| 2 | 300 mcg (0.3 mg) between 5-unit marks | 6 units | |
| 3 | 400 mcg (0.4 mg) between 5-unit marks | 8 units | |
| 4 | 500 mcg (0.5 mg) | 10 units | |
| 5 | 600 mcg (0.6 mg) between 5-unit marks | 12 units |
Doses marked “between 5-unit marks” sit between the 5-unit lines on a 1 mL syringe; the 1-unit lines on a 0.5 mL or 0.3 mL syringe make them easier to read.
Units are for a 10 mg vial mixed with 2 mL of water. Change the vial in the calculator
Full protocol details
Other protocols described
- By body weight. The dose scales with body weight. It runs from 200 to 300 mcg under 150 lb, up to 600 mcg over 250 lb.
Mixing in the protocols: 10 mg vial + 2 mL bacteriostatic water · 10 mg vial is 5 mg CJC-1295 (no DAC) + 5 mg ipamorelin. 10 units = 500 mcg of blend (250 mcg of each). At 500 mcg of blend a day, a vial lasts about 20 days..
Standard protocol
General optimization and fat loss
- Dose
- 200–600 mcg of blend (100–300 mcg of each peptide)
- How often
- Once daily, every day
- Timing
- Fasted, at least 2 hours after eating; before bed on an empty stomach is described as the best single slot, and the usual one for fat loss
- Route
- Subcutaneous
- How long
- 12–16 weeks
- Break
- 4 weeks
Doses here are for the whole equal-parts blend: each dose is half CJC-1295 (no DAC) and half ipamorelin. The source protocols state figures per peptide.
By body weight
- Dose
- Under 150 lbs: 200–300 mcg; 150–200 lbs: 400 mcg; 200–250 lbs: 500–600 mcg; over 250 lbs: 600 mcg (blend)
- How often
- Once daily
- Timing
- Fasted, at least 2 hours after eating
- Route
- Subcutaneous
- How long
- 12–16 weeks
- Break
- 4 weeks
Blend totals. Per peptide: 100–150, 200, 250–300 and 300 mcg.
Split dosing (advanced)
Two GH pulses a day
- Dose
- 200–300 mcg of blend per dose (100–150 mcg of each), twice a day
- How often
- Twice daily
- Timing
- Morning fasted, and again before bed
- Route
- Subcutaneous
- How long
- 12–16 weeks
- Break
- 4 weeks
Blend totals; 400–600 mcg of blend across the day.
Muscle-focused timing
Muscle and IGF-1 conversion
- Dose
- 200–600 mcg of blend (100–300 mcg of each peptide)
- How often
- Once daily
- Timing
- Morning, fasted, about 30 minutes before eating, so the meal's insulin drives the conversion of GH to IGF-1
- Route
- Subcutaneous
- How long
- 12–16 weeks
- Break
- 4 weeks
Same dose as the standard protocol; only the timing changes. The fasting rule still applies.
Cycle
12–16 weeks; 4 weeks
When a step up happens
User reports describe stepping up only after progress has stalled for two weeks or more, and only if the previous step was tolerated. Everyone is different.
Timing: Fasted, at least 2 hours after eating; before bed on an empty stomach is described as the best single slot, and the usual one for fat loss.
Peptide calculator
Already filled with this vial. Change anything you like.
How much is in your vial?
Check the label. The most common strengths:
Every 10 units = 0.4 mg.
5 units. 2.5 mL of BAC water
How the vial is mixed
The powder has to be dissolved in bacteriostatic (BAC) water before use. For a 10 mg vial this page uses 2 mL, which puts the usual dose on a round syringe mark: every 10 units is 500 mcg.
 STEP 1Wipe both topsAlcohol pad on the peptide vial and the BAC water vial.
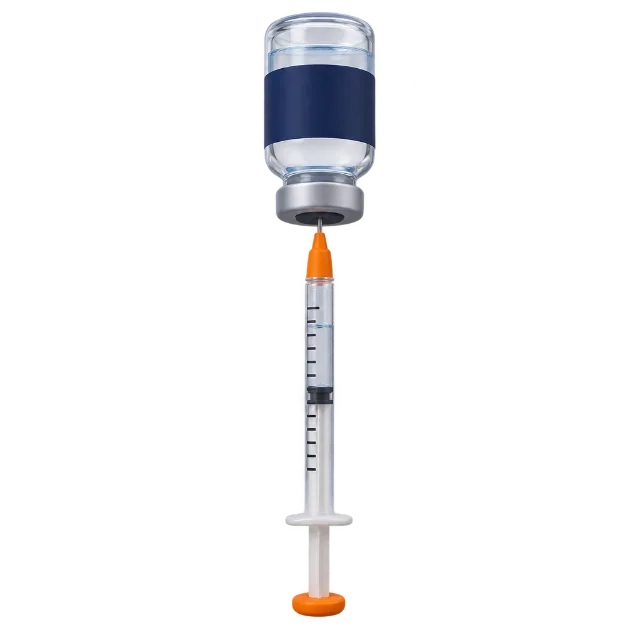 STEP 2Draw 2 mL of waterThat’s 2 full 1 mL syringes.
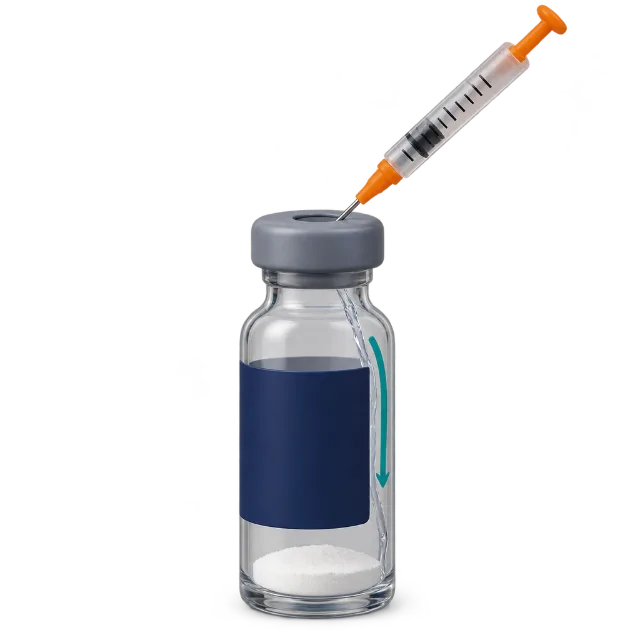 STEP 3Add it slowlyAim at the glass wall, not at the powder.
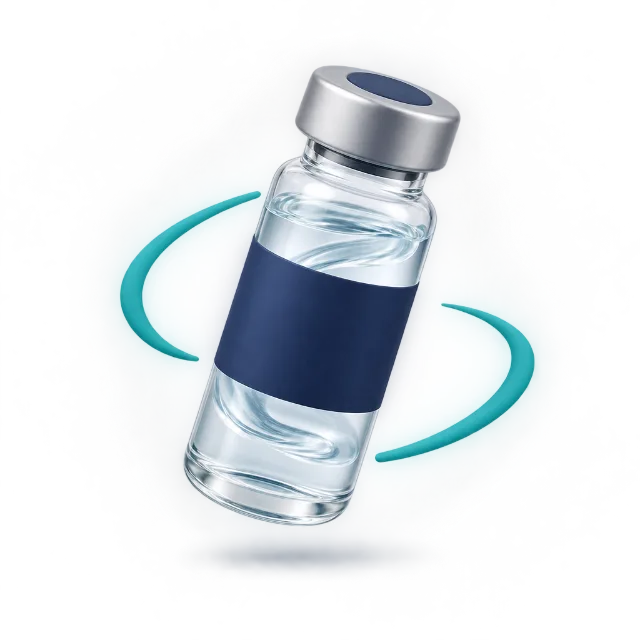 STEP 4Swirl, don’t shakeRoll gently until clear. Refrigerate after.
What to watch for
- Redness where the injection goes in, and flushingReported by users
- Mild water retentionReported by users
- Tingling or numbness in the handsReported by users
- Vivid dreams or broken sleep in the first weeksReported by users
- A faster heart rate, cited in an FDA safety reviewStudied in humans
Not for anyone with active cancer or tumors, diabetic eye disease, poorly controlled diabetes, or who is pregnant or breastfeeding. Talk to a doctor first, especially with diabetes, carpal tunnel, heart problems or any past cancer.
Reasons to get medical help right away: trouble breathing, swelling of the face or throat, chest pain, fainting, or any severe or worrying reaction.
Full side-effect list and who should avoid it
In published research
- CJC-1295 with DAC at 30–60 mcg/kg: well tolerated, with transient injection-site reactions, flushing and headache
- Ipamorelin: no meaningful rise in cortisol, prolactin or ACTH, even at doses well above those needed for GH release
- The FDA's safety review cites serious adverse events, including increased heart rate with CJC-1295 and a death in a published study of intravenous ipamorelin
What users report
- Common, usually gone within 2 weeks: injection-site redness, mild water retention, brief tingling or numbness in the hands, flushing, vivid dreams, lightheadedness at higher doses
- Less common: headache, mild hunger, early tiredness, temporary swings in blood sugar
- Described as signs the dose is too high: persistent numbness or tingling, carpal tunnel symptoms, joint swelling, facial puffiness. Users describe lowering the dose or pausing when these appear
Not for
- Active cancer or tumors; any history of cancer is described as needing an oncologist's clearance
- Diabetic retinopathy
- Diabetes that is not well controlled
- Pregnancy or breastfeeding
Use caution with
- Type 2 diabetes or prediabetes
- History of carpal tunnel syndrome
- Heart disease or high blood pressure
- Kidney or liver disease
- Insulin and oral diabetes medicines, which may need adjusting
- Glucocorticoids, which blunt the GH response
- Injected GH or IGF-1
- Bloodwork described around use: IGF-1 (the main marker), fasting glucose and HbA1c, and a standard metabolic panel
- Storage: powder at room temperature or refrigerated before mixing; after mixing, refrigerated at 2–8°C (36–46°F), not frozen, and used within 4 to 6 weeks
How the body handles it
- Ipamorelin: half-life about 2 hours; GH peaks about 40 minutes after a dose
- CJC-1295 without DAC: clears within minutes
- CJC-1295 with DAC (not in this blend): half-life 5.8 to 8.1 days; GH raised for 6 days or more and IGF-1 for 9 to 11 days
Supplies
What 12 weeks of the schedule above takes, counted dose by dose.

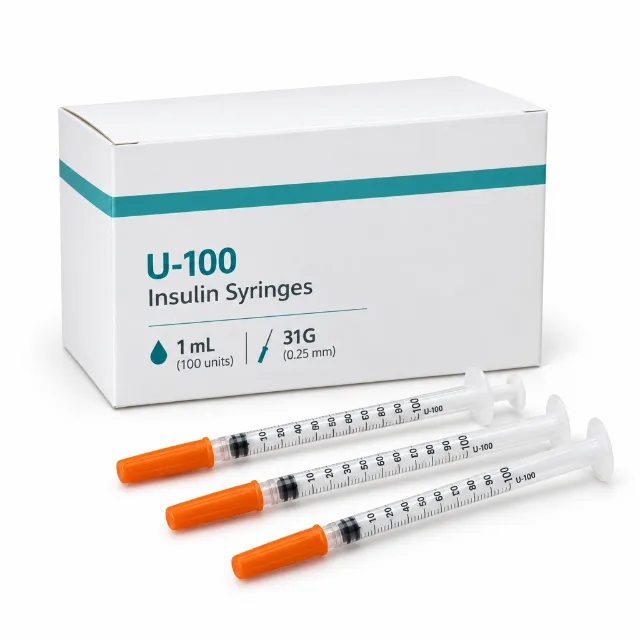

By clicking this link, WikiPep may receive a commission.
Stacking
What the community pairs with CJC-1295 / Ipamorelin, and why. None of these pairings has been tested in a trial.
- Testosterone therapyReported by users
The effects are described as complementary, with no interaction described. Users on testosterone therapy especially notice the faster recovery.
Also used alongside it, with no interactions described: GLP-1 drugs such as semaglutide, tirzepatide and retatrutide, BPC-157 and TB-500, and MOTS-c and SS-31.
Not combined with: Injected growth hormone or IGF-1, because rising IGF-1 switches on the body’s brake on both signals the blend uses.
Go deeper
Every study, community report and source behind this page.
What the studies show15 findings, each with its evidence label
Status, October 2026. Neither CJC-1295 nor ipamorelin is FDA-approved; CJC-1295 development stopped in phase 2, ipamorelin's phase 2 trials for post-surgery bowel recovery ended for lack of efficacy, and an FDA advisory committee voted against adding either to the compounding bulks list (CJC-1295 forms 0–13 or 1–12 on Dec 4, 2024; ipamorelin 0–12 on Oct 29, 2024). Source
How it works
The body releases GH in pulses. The largest comes during deep sleep, roughly 10 p.m. to 2 a.m., with smaller pulses after hard training and during fasting. Three signals set the rhythm: GHRH tells the pituitary to make and release GH, ghrelin releases what is stored, and somatostatin acts as the brake.
CJC-1295 acts on the GHRH receptor. Ipamorelin acts on the ghrelin receptor (GHS-R1a) and is described as also easing the somatostatin brake. GHRH is described as raising the number of cells releasing GH, and ghrelin mimics as raising the output of each cell. In a human study, combining the two signal types released GH synergistically, through independent pathways.
The liver turns GH into IGF-1igf-1A growth factor the liver makes in response to growth hormone. Blood tests use it to track growth-hormone activity., the molecule behind most of GH's downstream effects, and that step needs insulin. Because the pituitary is still making the decision, the body's own feedback loop stays in place, unlike with injected GH. A human study of the DAC form found the natural pulse pattern kept its frequency and size; whether the no-DAC form with ipamorelin does the same has not been tested.
Benefits
Each one carries an evidence label, so you can see how much is actually known.
Higher GH and IGF-1
In healthy adults, a single dose of CJC-1295 with DAC raised GH 2 to 10 fold and IGF-1igf-1A growth factor the liver makes in response to growth hormone. Blood tests use it to track growth-hormone activity. 1.5 to 3 fold, and with weekly doses IGF-1 stayed above baseline for up to 28 days. This is the long-acting form, not the one in the blend. source
Clean GH release
In a selectivity study, ipamorelin released GH without raising ACTH or cortisol, even at more than 200 times the effective dose. source
Better sleep
Usually the first change users describe, within the first 1 to 2 weeks.
Faster recovery
Users describe less soreness and quicker recovery after 2 to 4 weeks, which they link to higher GH and IGF-1.
Fat loss
GH is known to drive fat breakdown through hormone-sensitive lipase. Users describe visible changes around weeks 8 to 12.
Skin, joints and tendons
Users describe changes over months 3 to 6, which they attribute to collagen.
Clarity, focus and mood
Reported by users; research here is thin.
What the science shows
CJC-1295 with DAC in healthy adults (human, 2006)
Studied in humansTwo randomized, placeboplaceboAn inactive version given to some trial participants so the real effect can be measured fairly.-controlled, double-blind trials in adults aged 21 to 61. One injection under the skin raised GH 2 to 10 fold for 6 days or more and IGF-1igf-1A growth factor the liver makes in response to growth hormone. Blood tests use it to track growth-hormone activity. 1.5 to 3 fold for 9 to 11 days. Half-lifehalf-lifeHow long it takes for half of a compound to leave the body. A longer half-life usually means less frequent dosing. was 5.8 to 8.1 days. No serious adverse reactions at 30 or 60 mcgmcgMicrogram, one thousandth of a milligram. 1 mg = 1,000 mcg./kg. This is the long-acting DAC form. source
GH pulses under continuous stimulation (human, 2006)
Studied in humansWith CJC-1295 with DAC, pulse frequency and size did not change, while trough GH rose 7.5 fold, mean GH 46% and IGF-1 45%. source
Ipamorelin dose-escalation (human, 1999)
Studied in humansIn 40 healthy men, ipamorelin had a half-life of about 2 hours, GH peaked about 40 minutes after dosing, and the response rose with dose. source
Ipamorelin selectivity (1998)
Studied in animals or labNo ACTH or cortisol release at any dose tested, including more than 200 times the dose needed for GH release. source
GHRH and GHRP together (human, 1990)
Studied in humansIn 18 healthy men, a submaximal dose of a GH-releasing peptidepeptideA short chain of amino acids. Proteins are long chains; peptides are short ones, usually under 50 amino acids. combined with GHRH released GH synergistically, through independent pathways. source
Short-term desensitization (lab, 1991)
Studied in animals or labIn pituitary cells exposed to a related GH-releasing peptide, the drop in response after a dose recovered fully within 60 minutes. source
Long-term desensitization (human, 1998)
Studied in humansIn 12 older adults on twice-daily hexarelin, a related GH-releasing peptide, the GH response fell significantly by week 16 and returned to baseline after 4 weeks off. source
What has not been studied
UnknownNo randomized trial has tested the combination in healthy adults, and no study has measured body composition, strength, recovery or performance from it in trained adults. The case for the blend rests on each compound's own data and the known pathway synergy.
What the community reports6 user reports, a timeline and 5 pairings
What to expect
Sleep is the first change most users describe. Some have temporary sleep disruption that settles by weeks 4 to 6.
Reported by usersRecovery between sessions is described as improving.
Reported by usersFat loss starts to become visible, usually when diet and training are in place.
Reported by usersSkin, joint and connective-tissue changes are described. Over 16 to 24 weeks, much of the fat loss is reported toward the end of the cyclecycleA planned period of use followed by a break, written as weeks on / weeks off..
Reported by usersThe blend is described as an optimization tool for sleep, recovery and body composition. It is not described as a replacement for testosterone therapy or anabolic steroids for building muscle, and users on testosterone therapy report sleep gains with little change in muscle or strength.
What people report
Gathered from user communities. Anecdotal: useful for what to expect, not proof.
Sleep
The most common report, usually within 1 to 2 weeks. Some describe waking 2 to 3 times a night in weeks 3 to 4, settling by weeks 4 to 6. Vivid dreams are common early on.
Body composition
Less abdominal fat and more definition, arriving slowly over 16 weeks or more. The best results are described at 4 to 6 months with diet and training in order.
Recovery
Less soreness and the ability to train more often within the first month, noticed especially by people on testosterone therapy.
Skin and joints
Better skin elasticity and more comfortable joints and tendons after 3 months or more.
Compared with tesamorelin
Users tend to prefer the blend for general optimization and muscle, and tesamorelin when visceral fatvisceral fatFat stored deep around the organs, as opposed to the fat under the skin. is the specific focus.
Side effects
Injection-site redness, mild water retention, tingling or numbness in the hands and flushing, mostly fading within 2 weeks. Higher doses bring more water retention, carpal tunnel symptoms and joint swelling.
Stacking
How it is described alongside other compounds.
Testosterone therapy
No interaction concerns described; the effects are described as complementary.
GLP-1 drugs (Retatrutide, Semaglutide, Tirzepatide)
No interaction concerns described. The one point raised is appetite: if food intake drops too far, the conversion of GH to IGF-1 can suffer.
BPC-157 and TB-500
No interaction concerns described. Those peptides have no fasting rule, so the GH blend keeps its own fasted schedule.
MOTS-c and SS-31
No interaction concerns described; they work on different targets.
Injected GH or IGF-1
Listed as a combination not to run. Rising IGF-1 triggers somatostatin, which blunts both pathways the blend relies on. When switching from IGF-1 to the blend, protocols allow 2 to 3 days for it to clear.
Common questions10 questions
Common questions
Is CJC-1295 without DAC the same as Mod GRF 1-29?
Yes, two names for the same short-acting GHRH analog. Strictly, the name CJC-1295 belongs to the long-acting DAC version tested in the human trials.
Once a day, or split?
Once daily is the standard protocol, with bedtime on an empty stomach described as the best single slot. Splitting into a morning and a bedtime dose is described as catching two GH peaks.
Why does fasting matter?
Insulin suppresses GH release from the pituitary, so protocols place the dose at least 2 hours after eating.
Can CJC-1295 be run without ipamorelin?
It can, but the dual-pathway synergy that is the point of the blend is lost.
This blend or tesamorelin?
The blend is described for overall optimization; tesamorelin when visceral fat is the main goal.
How long until results?
Users describe sleep changes at 1–2 weeks, recovery at 2–4, body composition at 8–12, and connective tissue at 3–6 months.
Does it need days off each week?
The common 5-on, 2-off pattern is described as unnecessary. Short-term desensitization clears in about 60 minutes in lab work, and longer-term desensitization built up over about 16 weeks in a human study of a related peptide and recovered after 4 weeks off. That is the reasoning behind daily dosing for up to 16 weeks, then 4 weeks off. Dosing 5 days a week cuts cost by about 30%, and is described as a budget choice only.
Will it replace testosterone therapy for muscle?
No. It is described as helping recovery and optimization, not building muscle the way anabolic hormones do.
What does “minimum effective dose” mean?
It is the lowest dose that still produces the effect someone is after. User reports describe starting there and staying there for as long as it keeps working, rather than climbing toward the top of the range. Side effects tend to rise with dose, and the top of each range on this page is a ceiling people report, not a target.
When does the dose go up?
There is no trial schedule for CJC-1295 / Ipamorelin. User reports describe staying on a dose while it is still working, and moving up only after progress has stalled for two weeks or more and side effects have settled. There is no prize for getting to the top dose fast. These are not quick fixes: most of what people report builds over weeks, not days.
Source material7 studies and documents
References
- Teichman SL, Neale A, Lawrence B, Gagnon C, Castaigne JP, Frohman LA. J Clin Endocrinol Metab. 2006;91(3):799-805. pubmed.ncbi.nlm.nih.gov/16352683/…
- Ionescu M, Frohman LA. J Clin Endocrinol Metab. 2006;91(12):4792-4797. pubmed.ncbi.nlm.nih.gov/17018654/…
- Gobburu JV, Agerso H, Jusko WJ, Ynddal L. Pharm Res. 1999;16(9):1412-1416. pubmed.ncbi.nlm.nih.gov/10496658/…
- Raun K, Hansen BS, Johansen NL, Thogersen H, Madsen K, Ankersen M, Andersen PH. Eur J Endocrinol. 1998;139(5):552-561. pubmed.ncbi.nlm.nih.gov/9849822/…
- Bowers CY, Reynolds GA, Durham D, Barrera CM, Pezzoli SS, Thorner MO. J Clin Endocrinol Metab. 1990;70(4):975-982. pubmed.ncbi.nlm.nih.gov/2108187/…
- Blake AD, Smith RG. J Endocrinol. 1991;129(1):11-19. pubmed.ncbi.nlm.nih.gov/1674284/…
- Rahim A, Shalet SM. Growth Horm IGF Res. 1998;8 Suppl B:141-143. pubmed.ncbi.nlm.nih.gov/10990150/…
Related
What is CJC-1295 / Ipamorelin?
The blend pairs two growth-hormone secretagogues, compounds that prompt the pituitary to release growth hormone (GH). CJC-1295 without DAC, also called Mod GRF 1-29, is a copy of GHRH, the brain's release signal. Ipamorelin copies ghrelin, the hormone that triggers release of stored GH. The no-DAC form clears within minutes, so GH comes out in short pulses. The DAC form, which carries the name CJC-1295 in the human trials, lasts about a week. The two forms behave differently, and results from one do not carry over directly to the other. Neither peptidepeptideA short chain of amino acids. Proteins are long chains; peptides are short ones, usually under 50 amino acids. is FDA-approved. CJC-1295 development stopped in phase 2phase 2A mid-stage human trial that tests dose and early effect in hundreds of people. Phase 3 confirms results in thousands., ipamorelin's phase 2 trials for bowel recovery after surgery ended for lack of efficacy, and an FDA advisory committee voted against adding either to the compounding bulks list in late 2024.
What people look into CJC-1295 / Ipamorelin for
Every line carries an evidence label, so you can see how much is actually known.
Higher GH and IGF-1igf-1A growth factor the liver makes in response to growth hormone. Blood tests use it to track growth-hormone activity.: In healthy adults, a single dose of CJC-1295 with DAC raised GH 2 to 10 fold and IGF-1 1.5 to 3 fold, and with weekly doses IGF-1 stayed above baseline for up to 28 days. This is the long-acting form, not the one in the blend.source
Studied in humansClean GH release: In a selectivity study, ipamorelin released GH without raising ACTH or cortisol, even at more than 200 times the effective dose.source
Studied in animals or labBetter sleep: Usually the first change users describe, within the first 1 to 2 weeks.
Reported by usersFaster recovery: Users describe less soreness and quicker recovery after 2 to 4 weeks, which they link to higher GH and IGF-1.
Reported by usersFat loss: GH is known to drive fat breakdown through hormone-sensitive lipase. Users describe visible changes around weeks 8 to 12.
Reported by usersSkin, joints and tendons: Users describe changes over months 3 to 6, which they attribute to collagen.
Reported by usersClarity, focus and mood: Reported by users; research here is thin.
Reported by usersMix and measure: a 10 mg vial
Go deeper
How it works, in plain words
The body releases GH in pulses. The largest comes during deep sleep, roughly 10 p.m. to 2 a.m., with smaller pulses after hard training and during fasting. Three signals set the rhythm: GHRH tells the pituitary to make and release GH, ghrelin releases what is stored, and somatostatin acts as the brake.
What did the study measure?
No single study is featured for CJC-1295 / Ipamorelin; the human trials are linked from the uses above.
Sources
Side effects and who should avoid it
Side effects and limits, stated plainly. If anything here applies to you, talk to a doctor first.